
CT protocol basics
A CT protocol is a chain of decisions: beam energy, photon count, table speed, coverage and how raw data become images. Every choice trades image quality against dose or time, and only some of them can be changed after the scan.
By the ScanFlo Editorial Team · Updated
In this section · CT fundamentals
A CT protocol is the saved set of parameters for one examination: tube voltage (kV), tube current and rotation time (mAs), pitch, detector collimation and scan range for the acquisition, and kernel, slice thickness and window for the reconstruction. The acquisition parameters decide how many photons pass through the patient, and so the dose and the noise. The reconstruction parameters decide how those data become images, and you can change them afterwards without scanning again.
| Parameter | What it controls | Typical or reference value |
|---|---|---|
| Tube voltage (kV) | Beam energy: penetration, iodine contrast, noise | 120–140 kV routine; 80–100 kV for some contrast and paediatric work |
| Tube current × time (mAs) | Number of photons: noise and dose | Set by automatic exposure control; not comparable between scanner models |
| Effective mAs | mAs ÷ pitch, shown on some consoles | Held constant by the scanner as pitch changes |
| Pitch | Table travel per rotation ÷ total beam width | 1 = contiguous; <1 overlap; >1 gaps |
| Rotation time | Speed and temporal resolution | 0.3–0.4 s on multidetector scanners |
| Collimation (N × T) | Rows used × row width: coverage per rotation and thinnest slice | Up to 64 or more active rows |
| Scout (topogram) | Scan range and AEC input | Static tube, about 120 kV, 50–100 mA |
| Reconstructed slice | Detail vs noise | ≤1 mm for reformats; thicker for reading |
| Kernel | Sharpness vs noise | Soft for soft tissue; sharp for lung and bone |
Values from the IAEA Diagnostic Radiology Physics handbook (chapter 11: tube voltage, rotation time, rows, scout and slice thickness) and AAPM Report 96 (pitch, mAs and effective mAs).
How a CT protocol runs, in order
- STEP 01PositionPatient on the table; start position set with the positioning lights.
- STEP 02ScoutLow-dose topogram; sets the range and feeds exposure control.
- STEP 03RangeStart and end set to the indication, nothing more.
- STEP 04AcquirekV, mAs or AEC, pitch, rotation, collimation.
- STEP 05ReconstructKernel, slice thickness, increment, reformats.
- STEP 06WindowSoft tissue, lung or bone, matched to the question.
Tube voltage and mAs: energy and quantity
kV sets the energy of the photons. The IAEA handbook describes 120–140 kV as the usual choice for good transmission and detector signal, with 80–100 kV useful for contrast-enhanced and paediatric studies (§11.6). Lower kV makes iodine look brighter but lets fewer photons through a large patient, so it needs care.
mAs sets the number of photons. Dose rises in proportion to it; noise falls with its square root, because X-ray quantum noise follows Poisson statistics (IAEA, §4.5.1). Halve the mAs and the noise goes up by √2, about 41%. The IAEA handbook shows the effect with the same liver scan simulated at 100%, 75%, 50% and 25% of the tube current: the low-contrast lesions fade as the noise rises (Fig. 11.19).
On a modern scanner you rarely type a fixed mAs. Automatic exposure control reads the scout and adjusts the tube current along the body and around it. AAPM Report 96 is blunt that this does not reduce dose by itself: it delivers whatever image quality you ask for, so the reference setting you choose is the real dose decision.
Pitch, collimation and rotation time
Pitch is table travel per rotation divided by the total nominal beam width. At pitch 1 the beam edges meet; below 1 they overlap and tissue is irradiated more than once; above 1 there are gaps (AAPM Report 96; Radiopaedia, Pitch). Higher pitch covers the body faster, which helps breath-holds and contrast timing.
One catch. Several consoles show effective mAs (mAs ÷ pitch) and quietly raise the tube current when you raise the pitch, to keep noise constant. On those systems, changing pitch alone barely changes the dose (AAPM Report 96). Collimation (rows × row width) decides how much anatomy each rotation covers and the thinnest slice you can reconstruct later. Rotation time, 0.3–0.4 s on multidetector scanners according to the IAEA handbook, sets how quickly the scan is over and how well it freezes motion.
Reconstruction: the half you can redo
The same raw data can be reconstructed with a soft kernel for the mediastinum and a sharp kernel for the lungs, in thin slices for reformats and thicker slices for reading. The IAEA handbook shows a head reconstructed both ways: the soft kernel suits brain and blurs bone, the sharp kernel suits bone and makes the brain noisy (Fig. 11.22). Window settings then map Hounsfield units to grey. Radiopaedia lists brain W80/L40, mediastinum W350/L50, lungs W1500/L−600 and bone W1800/L400, and notes that these vary between institutions (Windowing (CT)). More on this in reconstruction, kernels and windows.
ScanFlo CT · head routine
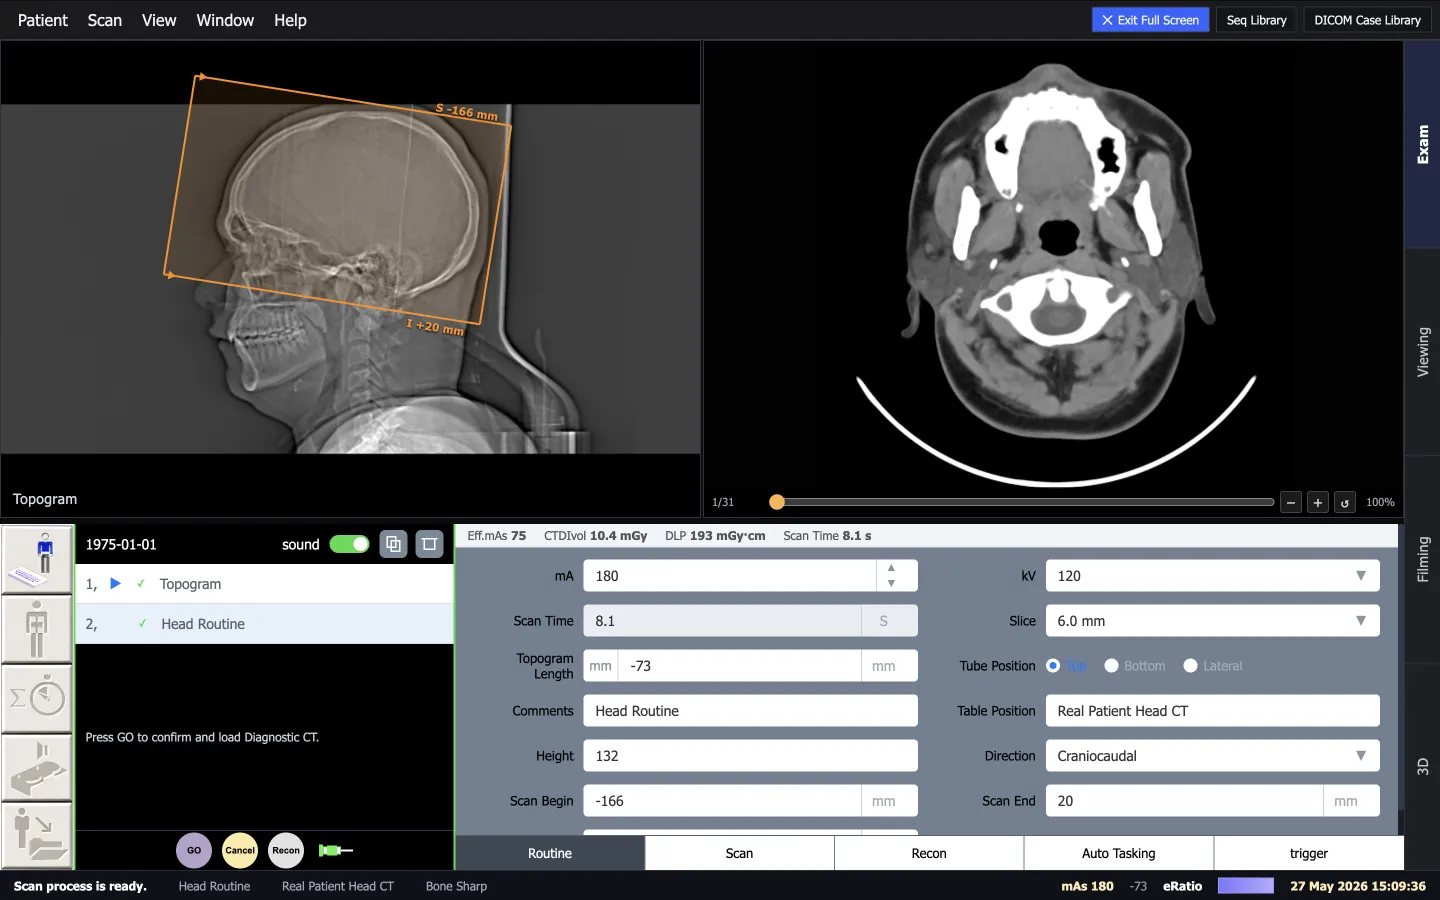
Worked example: reading the console before you scan
The screenshot above is a head routine on the ScanFlo CT simulator. The parameter card reads 120 kV and 180 mA, and the header shows effective mAs 75, CTDIvol 10.4 mGy and DLP 193 mGy·cm. The planned range runs from −166 mm to +20 mm, which is 186 mm or 18.6 cm.
Check the arithmetic: DLP = CTDIvol × scan length = 10.4 × 18.6 ≈ 193 mGy·cm, which matches the console. Now drag the lower edge of the range down by 5 cm. CTDIvol stays at 10.4 mGy, because it does not depend on length, but DLP rises to 10.4 × 23.6 ≈ 245 mGy·cm, an extra 27% for anatomy nobody asked for. Treat these figures as teaching values for the arithmetic; real protocols are judged against national reference levels such as the UK NDRLs, covered in CTDIvol and DLP.
Common mistakes
- Scanning more than the indication. Extra range adds DLP in direct proportion and gives the reader nothing.
- Comparing mAs between scanners. The same mAs gives different dose and noise on different models and at different kV.
- Raising pitch to save dose on a console that holds effective mAs constant. The tube current rises to compensate.
- Reading soft tissue on a sharp kernel, or bone on a soft one. Reconstruct both rather than compromising on one.
- Treating automatic exposure control as a dose saver on its own. Its reference setting decides the dose.
These follow from AAPM Report 96 and chapter 11 of the IAEA handbook. Contrast phase timing is its own topic: see contrast timing and bolus tracking.
Try it in ScanFlo: Run the chest case and reconstruct the same acquisition twice: soft kernel with a mediastinal window, then sharp kernel with a lung window. Same photons, two different diagnostic worlds. See ScanFlo CT →
Frequently asked questions
What are the main CT scan parameters?
On the acquisition side: tube voltage (kV), tube current and rotation time (together the mAs, usually set through automatic exposure control), pitch, detector collimation and scan range. On the reconstruction side: kernel, slice thickness and increment, and the display window. The acquisition parameters set dose; the reconstruction parameters can be changed afterwards from the same raw data.
What is pitch in CT?
Pitch is the table travel per gantry rotation divided by the total nominal beam width. A pitch of 1 means the beam edges just meet from one rotation to the next; below 1 they overlap, above 1 they leave gaps.
What is effective mAs?
Effective mAs (also shown as mAs per slice) is the true mAs divided by the pitch. Scanners that display it keep image noise roughly constant when you change pitch by adjusting the tube current behind the scenes, so changing pitch alone may not change the dose.
Why is 120 kV so common?
A relatively high tube voltage (120 to 140 kV) gives good X-ray transmission and enough detector signal for most adult body work. Lower voltages (80 to 100 kV) can suit contrast-enhanced studies and children, because iodine attenuates relatively more at lower energy.
Does halving the mAs halve the dose?
Yes, at fixed kV and pitch the dose is proportional to mAs. Image noise rises by about 41% (a factor of √2), because noise follows the square root of the number of photons.
Sources
Every figure on this page links back to one of these.
- Dance DR, Christofides S, Maidment ADA, McLean ID, Ng KH (eds). Diagnostic Radiology Physics: A Handbook for Teachers and Students. IAEA, Vienna, 2014. Chapters 4 and 11
- AAPM Report No. 96. The Measurement, Reporting, and Management of Radiation Dose in CT. American Association of Physicists in Medicine, 2008
- Radiopaedia. Windowing (CT)
- Radiopaedia. Pitch (CT)
- UK Health Security Agency. National Diagnostic Reference Levels (NDRLs) from 11 December 2025. GOV.UK